Sunday, February 8, 2015

27 Weeks, 6 Days

Thursday, we had our second appointment at Mott's. We dropped Carsyn off at a family friends house, her first time being baby sat at someone else's house with someone new. She did great! Didn't cry once, and made a new doggy friend!

First stop, we had a fetal echo, and met with the second cardiologist. She sat down and gave us some more details about fetal intervention and explained the risks again, all of which we understood, but they had to be said by her again. There were some things we did find out about Kennedy's heart that we didn't know before.

The anatomy of Kennedy's heart isn't normal, as we already know, but there is more about the anatomy that is different, but it doesn't change her health. In a normal heart, there are typically 4 pulmonary veins that empty into the left atrium (upper chamber) from the lungs, and from there the blood would typically go into the left ventricle to the aorta to be pumped to the body. In Kennedy's heart, the 2 veins on the right side actually wrap around her heart, connect with the 2 veins on the left side to make one big vein that empties into the atrium. Because of the way those veins lead to her left atrium, the only way they can do intervention is if they enter through the right side of her heart, go through the right atrium and into the septum to place a stent and make the right and left atriums flow together. This adds a little challenge to the intervention, because instead of them being able to enter either side of the heart, they can only enter from the right side. She has to be laying perfect with her right side up in order for them to be able to access her septum. Her heart is also missing the mitral valve on the left side, which is the cause of the hypoplastic left heart.

Normal Heart Anatomy (showing the pulmonary veins on the left and right sides)

We asked the cardiologists many questions about the intervention and the way they would go about doing it. She explained to us all the people that would be in the operating room at once:
  • Two high risk OB's
  • Two cardiologists
  • Two pediatric cardiologists
  • Two anesthesiologists
  • Our nurse practitioner
  • Our neonatal/perinatal specialist
  • And that's all I know for sure, but I'm sure there are more.
Each person in the operating room have their own jobs. The OB's are the hands in the procedure, directing the needle into the heart. There are two people running the sonogram and directing the OB's where the needle needs to go. Another person will "wire" the needle with the stent and balloon, one will push the button to inflate the balloon, one will record the numbers, and so on and so forth. Their fetal intervention team is the team that does all interventions at Mott, and they all were very confident in each other and the way they work together as a team. That was the one thing I heard that really made my decision from the facts standpoint. I've been a part of many teams in my life, and if you can rely and count on your team members, you typically are much more successful. Every other part of the decision has been based off the gut feeling I have that this is best. I know God has his hand guiding us in every way.

The process of fetal intervention could last for hours. Once I am prepped and taken to the OR, they will check to see where Kennedy is laying. If she isn't laying in the right position I will have to move around somehow to try and get her to lay perfect. I won't get an epidural until she is laying in the right position. Blaine isn't permitted into the operating room, so he will have to wait, which could be 6+ hours. Once she is in the right position, I will get my epidural and they will give her a shot to make her stop moving and temporarily paralyze her. I will be awake the entire time, unless I need something to sedate me to help me relax a little bit. After they are done, they will monitor her for about 20-30 minutes, which is the most critical time period, and watch for bleeding and other problems. Once my epidural wears off we will be free to go home. I won't be able to pick Carsyn up, or do any lifting that really uses my abdominals for a week. Although everything is so scary, I know God has placed us with these amazing doctors for a reason. I also keep telling Kennedy she is already such a strong little girl, and she can do anything. I truly do believe that.

After meeting with the cardiologist, we took a tour of the 3 floors we will staying on: the pediatric general care on the cardio floor, the maternity floor, and the Pediatric Cardiothoracic Unit (PCTU). We had another quick body ultrasound to see how she is growing (not that 2 weeks really makes much of a difference.) At that point, she was laying in the most perfect position for fetal intervention. We met with the OB and she explained her position of the intervention. She deals with the intervention things the most, then once the baby is born the cardiologists take over from there. I asked her if we should get an amniocentesis since they will be in there during intervention. I wanted her opinion because I wasn't sure if it would help at all in the long run. She said she had discussed with her team, and they all agreed that at this point and everything they have seen, they will do anything they can to help Kennedy. When you feel like it's the world at your back and you can only control so much anymore, it's a huge sigh of relief and an uplifting feeling knowing there are a handful of doctors that have committed themselves to do the best they can to save your child. There have been no major red flags of other disorders or anything to make them hesitant. Maybe once she is born, we will have some genetic testing just to try and help the research side of it and hope they can connect these heart defects with anything. As a family, we can fight for our own, but we can also try to help the next family, which was and still is us. Not only do we feel fetal intervention can really help Kennedy, if it is unsuccessful, we are praying our doctors can learn from our experience and better their procedures to help the next family. Their main goal is to try and give her sometime once she is born and to hope her lungs can develop a little more normal throughout the rest of her stay in my belly. We pray this will work and go at ease with everyone involved.

Fetal cardiac intervention is scheduled for Tuesday, February 24. Please say a prayer for us, especially to Kennedy to continue to fight, and all the doctors and hands involved.

We have another regular scheduled check up here in Lansing with the specialist, and another ultrasound on Monday, February 9. I have my gestational diabetes test then also...yuck. I love seeing our little girl so often, but I hate the nervousness that someone will see something else wrong.

February 7-14 This week is Congenital Heart Defects (CHD) Awareness Week! Please say a prayer for all families fighting CHDs, and if you find it in your heart to donate to any foundation/family with a CHD!

Join the Fight with Kennedy

"Every little bit makes a difference."

Also, I am challenging everyone who reads this to take a picture of your hand heart and post it in the comments of the blog AND on Facebook! We want to see everyones hand hearts! THEN challenge and tag 3 friends to do the same! Please help spread awareness!!!


My Hand Heart for Kennedy
Blaine's Hand Heart

Kennedy 28 Weeks
Carsyn and Lilah
Thank you everyone for following our story and for the prayers and support. May He bless you.

Monday, February 2, 2015

Slowly Moving....

Since my last appointments a couple weeks ago, we haven't had very much going on. Blaine has really been getting into indoor season. Carsyn and I have been able to make it to a couple meets. She loves going to them and running around. I really don't get to watch the athletes much, as I am busy chasing around my 'athlete in training', but it's still great to be able to get out of the house for a little.


We have our next appointment this Thursday, February 5, in Ann Arbor again. We will be meeting with the maternal/fetal medicine doctor for a consultation and possibly another full body ultrasound, and also have another fetal echo done with the cardiologists. Hopefully then we will find out the finalized date for fetal intervention so we can plan and prepare ourselves for this big step. Kennedy has been a wiggle worm. She's been stretching her little legs in there quite often the past couple days and it really hurts. I end up having to push her little feet back just to make her stop. I am glad she is spunky already. She responds to almost every push or touch to my belly.

Last week, we received a care package from Sisters By Heart, an organization to help families with babies with CHDs and HLHS. Whomever nominated us, a very big THANK YOU! We greatly appreciate it. I wanted to share what things came in the care package and maybe a little description as to why they would include that item in it...


  • A tote bag
  • A book for Carsyn
  • Matt Hammitt- All of Me CD
    • I have often found comfort in his CD already. Matt is a member for a Christian band called Sanctus Real. In 2010, his family found out their little boy, Bowen, had Hypoplastic Left Heart. He wrote an album throughout their journey, so most of the songs we can relate to very well. I highly suggest listening to the album (it can be found on YouTube), and also reading about their story. www.bowensheart.com
  • Swaddle blankets are used often as the babies can't wear clothing very often. It is a whole new challenge to learn to swaddle around tubes and wires, as I am sure Blaine will figure it out quickly and become a pro.
  • Coffee mug
  • Notebook
  • A STOP! sign to ask people to not touch the baby and to wash their hands before they do. I have never been a germ-a-phobe, but I think once Kennedy is here I will be.
  • Stress ball
  • Hand sanitizer and sanitizer lotion
  • A onesie donated by Pampers
  • Smiley face baby hospital gown
  • Pacifier babies must retain their sucking, so while she will have a feeding tube, pacifiers will be used often to keep her sucking.
  • Deck of cards
  • Baby socks
  • Baby leg warmers
  • Hat
  • Side snap (Kimono style) onesie
As it may not seem like much, it is so great having things we know we will need once Kennedy arrives. I never realized how hard it is to find side snap onesies/bodysuits that aren't plain white!!!

We are looking forward to Thursday to keep the ball rolling and to be able to see our sweet girl again! Thank you so much everyone for the prayers and support. We are really feeling it and cannot thank everyone enough!


February is Heart Awareness Month! Please wear RED to support and spread word on heart awareness!


God bless you all,

Ana

Saturday, January 24, 2015

Big Decisions

January 22 -- 25 Weeks, 5 Days


We had our first visit at Mott Children's Hospital in Ann Arbor. Blaine's parents came Wednesday night so they could stay with Carsyn while we were gone at our appointments. That night I woke up at 3:45AM. I don't know why it was such a big deal, but I was so worried because I had forgotten to change Carsyn's poopy diaper before bed. I think I was so worried because I was also so anxious for our appointments. I could't fall back asleep, so I got out of bed around 5:15 to get dressed. Once Blaine woke up and we were just about to walk out the door, I said I felt bad because I forgot to change Carsyn's diaper before she went to sleep so she's been sleeping in a poopy diaper all night. Blaine said he changed her before he put her in bed. Well shucks, all that worry for no reason!

Every single doctors appointment really puts me on edge. I do get worried of the bad news that could be said, as the past few appointments have snowballed with bad news after bad news. We arrived to Mott's a bit early, but it gave us a few minutes to find Blaine some coffee and find our way to our first appointment. There we had a full body ultrasound in fetal diagnostics. Blaine and I were both amazed with how nice all the equipment was. We have seen plenty of ultrasounds, and the pictures we were seeing was almost in ultra high definition. Once the tech was done, the maternal and fetal medicine doctor came in to talk with us about what she saw. She said she wanted to take a closer look at some things that she wasn't seeing clearly, oh great, here we go again. She began looking closely at Kennedy's lips and nose looking for deformations, then to her ears. She said everything was looking good, and she turned the picture to 3D. There she was, the most beautiful little girl I have ever seen, along with her big sister. It nearly brought tears to my eyes, and it really made my heartache. How can something so "perfect" be going through so much. I was so happy to see that face, nose, ears, and fingers. So perfect, so little. It brought me a sense of hope. Once we were done with the doctor, we met with a genetic counselor, which was very laid back. We then headed up to the 11th floor where the pediatric cardiac floor was located. Up next, a fetal echo. Blaine and I were both getting heavy eyes, and having the fetal echo done in a dark room wasn't helping at all. The bed I was laying on was so comfortable, and laying there watching the flutter of Kennedy's little heart on the screen was really making my eyes even more heavy. The cardiologist came in to take a look at some things for herself, then we sat down and discussed the next steps.

She confirmed the findings that Kennedy does in fact have an intact atrial septum. We have two choices: 1). Fetal Intervention or 2.) Surgery immediately when she's born. With both come many risks:

Fetal Intervention:

  • There is a 10% chance she would not survive after intervention.
  • I could go into preterm labor, and if she is premature, there would be almost no chance of saving her.
  • There are a few other complications that could happen, as they would be sticking a needle into a blood filled organ (her heart), and anything the needle would go through (my belly, the amniotic sac, her chest, and her heart), there is a possibility of bleeding and not being able to stop it.
  • As there are risks with any type of surgery, the risks to me are much less than the risks to her.
Immediate Surgery After Delivery
  • There is a 50% chance she would not survive, as babies with intact septums are born very sick and go downhill very quickly.
  • They would deliver her via C-Section (probably in the cath lab) then move her across the room and operate immediately as they would have to for any chance of survival.
  • Since these babies come out very sick, there is a chance she wouldn't be strong or big enough to make it through the first surgery.
As fetal intervention is still very new and very rare, it's still in an experimental stage. They aren't sure if there are any long term benefits to doing fetal intervention, but they believe that by doing so it prevents 8-10 weeks of damage to the lung vessels. If we do decide to go with the intervention, after delivery they would monitor her until they feel they are ready to operate. In the first surgery, they will look at her aorta and decide if it is capable of doing its job. If her aorta is big enough, she will have a pulmonary band placed on her pulmonary artery to regulate blood flow to the lungs. If her aorta is too small, she will have to have the Norwood procedure done. The Norwood is a higher risk surgery, as it is a bypass. Once they determine her aorta's status and give her the proper surgery, she will still be receiving the next two surgeries: Hemi-Fontan (Glenn) around 3 months and the Fontan between 18 months and 3 years. The cardiologist did say that both procedures have been successful, but ultimately we have to do what we feel is best for us.

Both scenarios absolutely terrify us. It's still hard to come to terms with the fact that I could lose my little girl. Blaine and I both feel as though we aren't quite ready to make a decision yet, but something is telling us to do intervention. I would do anything to give her one more chance to fight, anything. I pray God will take my hand and lead me to what is best for her. I already feel like He has pulled me in that direction, because it's not the "facts" or statistics that make me feel like this is best. It's the feeling in my heart and gut that this is what I must do. The cardiologist said they will be aiming to do intervention around February 24 (30 weeks). They still have to coordinate with all the doctors and make sure everyone is available and can be there on that day. We will plan and schedule the date for the intervention and begin the insurance pre-approval process. We will continue to pray and let God help us through this and make sure this is the best decision, and pray the insurance will cover as much of the surgery expense as possible, as this is one more major medical expense we will have to pay for a large chunk of that we weren't planning on. As hard as it is to try and not stress about money, which has not been easy for months since I haven't been able to find a job, this has really put the cherry on top. Money IS a big deal when it comes to the possible expenses we will have to face, and it is a reality we have to consider.

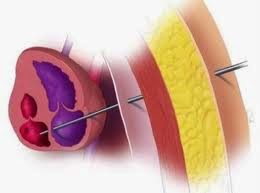
I am sure you all are wondering what the intervention process would be like for us. The surgery is an outpatient surgery. I would get an epidural, and they would just give me one dose and wouldn't keep administering more because they may need me to get up and move around to get her in the perfect position she needs to be in. Once she is there, they will give me more epidural, and give her a shot in the arm, butt, or leg (whichever is the easiest access to give her anesthesia, a sedative type drug to prevent her from moving, and something else to help with her healing). The doctors will place a large needle through my belly, through her chest cavity, and directly into her heart. They will blow up a tiny balloon connected to a wire through the needle, and place a shunt in the septum wall to keep it open. The doctors would monitor her for a few minutes and make sure blood is flowing through the hole (which they say can be seen immediately). The whole process is done using sonogram. The incision site on me would be so little there would only be one or two stitches, unless they use glue, and it's so little it can fit under a bandaid. From there, they continue to monitor her to make sure she isn't bleeding into the paracardial sac, or have any other complications. They would let my epidural wear off and once I can do all the things the epidural disrupts, I am free to go home. I would have to return to Ann Arbor within the next few days for them to check her again to make sure she is doing ok. I wouldn't be placed on bedrest or anything extreme for recovery, they recommend to take it easy for a few days following. Since every appointment is scheduled by the hospital, we don't really get to pick our days, and with the surgery we have to do it when all the doctors are open. Of course, the week they plan to do it is the week of indoor Big Tens in Cleveland. Blaine will probably have to leave that Wednesday, and won't be back until late Saturday. I am so thankful for the staff he works with and under and that they are allowing him to go to all of our appointments. I don't think I could go to them on my own or with anyone else and be ok. I pray we can have intervention the week before or that Tuesday they are planning on before he would have to leave. It's already so hard on him to have to leave at all, especially at such an important time.

Kennedy 25 Weeks
Fetal Cardiac Intervention 
Fetal Cardiac Intervention


I haven't been sleeping very well the past couple nights since our appointment at Mott's. I can't stop seeing her little face, and I think about her so often. I've felt so tired, but I can't get a good sleep. I can feel myself tossing and turning the whole night I am sleeping. This weekend I have kept myself decently busy. I had to work a MSU hockey game last night (Friday), one today, and I have a MSU women's basketball game tomorrow. Blake came and visited today, and watched Carsyn for us while Blaine was at Notre Dame for a meet and when I had to leave for the game. We've always managed to do everything with Carsyn on our own. I've only had people watch her a handful of times (all of which I can count on one hand, we may have hit two hands today and the majority when we are home for a few hours). Besides that, I've always taken her everywhere. I wish we could live closer to Blake. He has been one of my best friends since I have known Blaine. He probably knows a lot more about me than most brother-in-laws should know about their sister-in-law, but he's really been a saving grace in my life. Carsyn loves him so much. She used to cry just seeing him a few months back, so I am so happy she gets excited to see him. It's been an overwhelming week. As a new month is upon us, I keep thinking of everything that awaits us beginning February 1.

I want to thank everyone for keeping our family in their thoughts and prayers. Every prayer for our sweet Kennedy is special and we thank you so much. Please keep sharing our page and our fundraiser. "Every little bit makes a difference." I have had a few people reach out to me about our situation, one of those people has really made an impact in my life, and I am glad I can do the same for her. Please say a prayer for her as her little girl needs them desperately also.

Kennedy 25 Weeks

God Bless You All,

Monday, January 19, 2015

The Rollercoasters

As expected, my emotions are like a rollercoaster. Some days are very difficult and I am not sure how much more I can handle, other days I barely get by without tears, and then there are those days that aren't so bad. It's generally hard to deal with daily. The acceptance. The unknown. The questions. Not always do those things directly relate to Kennedy, but they can still be stressful, as almost everything seems slightly stressful nowadays. I feel like my to-do list has grown enormously and the deadline is already so near, but I have no idea how we are even going to be able to manage it all. Sometimes maybe I am being irrational, as my mind is someplace else, and although I think it may be important to do now, it probably is not. Hearing things I don't want to hear, in any sort of situation, is the most frustrating thing. Over the past month and a half, there have been more things I haven't wanted to hear, than things I have. I feel like a magnet to it, and there's no escaping. I pray and pray and pray that there will be a miracle. I know God will guide me in the right direction, but sometimes it's hard to give myself any credit. I often worry that I am not doing enough for Carsyn and am not being the parent she needs, especially when I have bad days. I know she is so happy and she has everything she needs, I just feel bad that my mind is often someplace else. I think the hardest part right now for me is I feel like I can't escape this. My growing belly is always there to remind me of this beautiful little girl, with an already broken heart, and it breaks my heart....every.single.time. I often find myself wearing Blaine's shirts, simply because they hide my belly. I don't feel that pregnancy glow that I felt with Carsyn, and I don't feel good in my maternity clothes, when most women feel beautiful. I'm scared people are going to stop me and comment on me being pregnant, just because I want to avoid that conversation. So many people ask how you're feeling and it's so hard for me to say I've been feeling good when emotionally I am a wreck. If I were to respond with an ok or an alright, there would be more questions. Physically, yes, I have been ok, emotionally it's been so hard, at least lately. The days I find myself feeling confident in my image, are usually my good days, but those days haven't been very often. As they say, "look good, feel good" and it hasn't been more true. Today has just been one of those cloudy feeling days, and thankfully Carsyn was great and played on her own (like she usually does), but she brought me many smiles when I needed them. Nothing makes me happier than knowing she is happy and so content with her life. She is going to be such a great big sister, with so much love.

Tomorrow I have an appointment with my OB for a regular baby check up. Although, most doctor appointments have made me apprehensive lately, I always look forward to having more answers. I will be happy once Thursday arrives, so we will have a better layout of the remaining months. I swear the past two weeks have been the slowest weeks of my life. It has felt slower than how I usually feel running a mile (and most people know that is pretty slow). I am praying for an easy appointment tomorrow, and hopefully it will brighten my spirits. I just don't want anymore surprises. I do know that these times will pass. I will have good and bad days, and I completely understand that, I just hope the brighter days come along soon and decide to stick around.

The support from everyone has been very overwhelming, in the best way possible. We are so blessed there are so many people praying for and thinking of us. Thank you everyone. We greatly appreciate you. May God bless you, and always watch over you, as you have done for us.

Psalm 46:1

Saturday, January 17, 2015

THANK YOU!!!

Wow! All we can say is thank you everyone for your kind thoughts, prayers, and donations! The past couple days have been so overwhelming (in the best way possible), as God is so amazing and has put all of you wonderful people into our lives! As the past week and a half has been emotionally draining and so stressful, the past two days have lifted me. Knowing there are so many loving and caring people, have made us feel so blessed. Blaine and I both apologize if we haven't responded to texts, messages, or comments. It's hard to try to respond to so many people at once, just know we thank you deeply from the bottom of our hearts and we cherish every single one of you!

The night I decided to publicly publish my blog, I had a lot of anxiety. I was relieved to finally be able to allow people in, and to learn about our situation, but I was also very much scared. Scared, I am not sure why, but I was.

Yesterday, Carsyn and I went to Blaine's track meet at Grand Valley State, and today, two of my big brothers (Chad and Ryan), along with their wife (Angie) and soon-to-be-wife (Rachel), took us and Blake to the Auto Show in Detroit. They even allowed Blaine and I to go out for a movie date, while they all got to spend time with Carsyn! It's been nice to be able to get out of the house for a little and not be constantly thinking of Kennedy (which I still do, but I don't feel so alone out in public). Through all these trying times, I am so thankful God and my Mom have given me the people I need. Obviously, my family (although they didn't have a choice), but mostly all of my in-laws. I love you guys so much!

To update everyone on "what's next," our first appointment at Mott Children's is scheduled for Thursday morning. We will be getting two separate fetal echos done, and meeting with one of the cardiologists. They want to get a better look at Kennedy's atrial septum, and I am sure we will discuss the next steps required. I am already so grateful for the kindness Mott's staff has showed us, and we haven't even begun there yet.

Once again, thank you so much everyone for joining us! Please keep those prayers coming, we are already feeling them!

So much love for you all and may God bless you,

Blaine, Ana, Carsyn, Kennedy, and Izzy (we can't ever forget the dog!)


Please keep sharing our fundraiser to help fight HLHS.
http://www.youcaring.com/medical-fundraiser/join-the-fight-with-kennedy-against-hlhs/292058

Wednesday, January 14, 2015

24 Weeks, 4 Days

This morning started out a little crazy. I woke up from a deep sleep around 9:30 when Blaine just walked out the door for work. I just wanted to lay there, but had a hunch to look at my phone, I had a bunch of text messages, two missed calls, and one voicemail, from the cardiologists office. I called her back immediately as she said the doctors thought they could squeeze us in today, a week earlier than expected before our appointment. She said they could get us in at 11:00, but had to arrive around 10:45 to get registered, it was now about 9:45. Carsyn was still in her bed playing. I had about 30 minutes to get her dressed, fed breakfast, me dressed, the dog out to potty, and us packed in the car to leave. As I'm running around the house trying to gather everything, and not forget all of Carsyn's snacks since I knew we would need something to keep her quiet, I kept thanking God that we will find out some answers. Answers that I have been very anxious about knowing. Throughout this journey I have had so many highs and lows emotionally. I know in my heart God has put us here for a reason, and I have kept my faith, even through the worst.

We did make it to the office just in time!

We met our pediatric cardiologist, and another pediatric cardiologist who would be running our fetal echocardiogram with the technician. I couldn't see much of anything, but could catch words and phrases here and there of what he was looking at. We then went into a conference room so he could explain his findings to us more in detail. He explained that Kennedy had HLHS with a Double Outlet Right Ventricle (DORV) and a possibility of an intact or highly restrictive atrial septum. This either made things better, or worse.


Double Outlet Right Ventricle (DORV)

Double Outlet Right Ventricle (DORV) is also a rare congenital heart defect, just like HLHS. In a normal heart, the aorta outlets from the left ventricle and pumps blood to the body and the pulmonary artery outlets from the right ventricle to pump blood to the lungs. In hearts with DORV, both of the arteries are connected to the right ventricle. In typical DORV cases, there is also a ventricular septal defect present. Kennedy's ventricular septum is intact, but with her HLHS, the left ventricle is too underdeveloped and small to hold and pump blood to the body. Best case scenario, if her aorta is big enough and strong enough, she will just need a pulmonary band to help regulate the blood flow to the lungs, but the right side would be the main pumping side that would be responsible for pumping blood to both the lungs and the body. This would replace the first stage surgery called the Norwood procedure. If her aorta is not efficient enough, she will still have to undergo the Norwood, the surgeons wouldn't know which one she would need until she had surgery and after she has been monitored after birth.


Intact or Highly Restrictive Atrial Septum

In fetuses, the atrial septum naturally has a defect or hole that allows the blood to freely flow between the atriums. This helps regulate the pressure in the lungs. Once a baby is born, the atrial septum usually closes on it's own due to pressure changes within the heart and lungs to create two separate atriums and four total chambers within the heart. If a fetus has a restrictive atrial septum, the pressure in the atrium becomes too great. Babies diagnosed with a restrictive septum have a higher mortality rate (50% survival rate).

After our discussion on the newest details, he still wasn't positive on Kennedy having a restrictive septum. He rushed the images to the other cardiologists in Ann Arbor to take a look so we could get some answers ASAP. If she did have a restrictive atrial septum, we had three options: the first of which is not an option in my book, to terminate the pregnancy; the second, to have a fetal intervention (surgery in-utero to open up the atrium wall using a needle through my belly wired with a balloon on the end, like an angioplasty); or the third, wait until she is born and rush her into surgery immediately. Once again, we walked out of the doctors with so many more questions and more concerns for our baby's future.

A couple hours later, the doctor calls to confirm his findings. I can still hear his voice over the phone, "The doctors in Ann Arbor confirmed what I thought. Intervention can happen between 28-29 weeks, and they said there's no need to rush in here this week. The nurse practitioners will call you with an appointment for sometime next week." Once we got off the phone, there I was again...blank. No emotions, feelings, or thoughts. How has something already so fragile gone through so much? The answers I needed to hear, were not the ones I wanted to hear. Another day with too many tears and more heartbreaking news.

I have been praying for guidance, for all the decisions I make, and pray they are the best for us. We have weighed the options for fetal intervention vs. postnatal surgery, and researched as much as we possibly could. The wait still sits between us and what's next, but I have a lot of faith we will do what's best. As I sit here tonight, I still feel all the love and support we have been blessed with, between family, friends, and acquaintances. Although, many of those people don't know our situation yet, it's amazing the people God places in your life, even those that you may have only said hi to once or twice in passing. I really do feel all the support we have been given thus far, and I pray we get our miracle for Kennedy.


Closed Fetal Cardiac Intervention

In the present review, “closed FCI” indicates mechanical interventions in which the uterus is not opened or accessed with a port ≥3 mm in diameter. In practice, closed FCI consists primarily of percutaneous interventions in which an 18- to 19-gauge needle is used to gain uterine and fetal access. The first reported case of closed FCI was a balloon aortic valvuloplasty performed in 1989.63 Since then, FCI has been reported in human fetuses with aortic stenosis (AS), HLHS with atrial septal restriction, pulmonary atresia or stenosis, and AV block.3–6,62 In 2000, we began a program for FCI, initially to treat fetal AS with evolving HLHS, then expanding to include HLHS with an intact or highly restrictive atrial septum, pulmonary atresia with an intact ventricular septum (PA/IVS) and evolving hypoplastic right heart syndrome, and structural anomalies causing hydrops.5–9,17,18 Since our first procedure, we have attempted FCI in more than 120 fetuses.
Typically, we perform FCI using a percutaneous ultrasound-guided approach with maternal and fetal anesthesia; in a minority of cases, laparotomy without hysterotomy is used to facilitate fetal imaging or access. All of the procedures we perform consist of opening an atretic or restrictive valve or septum, and instrumentation is limited and simple, with an access cannula, a guidewire, an angioplasty balloon and/or stent, and sometimes an additional needle to enter the heart or perforate an atretic valve or septum. With the exception of an 18-gauge curved-tip cannula that was developed specifically for FCI (SHARC Access Needle Set, ATC Technologies, Wilmington, Mass), we use off-label equipment that was designed for other applications and may limit technical options and potentially procedural feasibility.

Fetal HLHS With Intact or Highly Restrictive Atrial Septum

Although neonatal survival in infants with HLHS continues to improve, outcomes among certain subsets of patients remain poor; one of the strongest risk factors for early mortality is an intact or highly restrictive atrial septum.68,69 Although limited pulmonary venous egress may be well tolerated in utero, neonates with major septal restriction are at substantially higher risk of death than those without.67,68There are 2 primary problems associated with this condition: (1) Profound hypoxemia after birth due to restricted outflow from the pulmonary veins, which results in little effective pulmonary blood flow, and (2) chronic pulmonary venous hypertension in utero due to restriction to left atrial outflow, which results in pulmonary venous thickening68 and perioperative morbidity and mortality. Thus, even if postnatal opening of the atrial septum is rapid and effective, damage to the pulmonary vasculature may contribute to further mortality in the first few weeks or months of life.
In fetuses with HLHS and an intact atrial septum, FCI may improve both of the major problems posed by the restriction of pulmonary venous outflow. If the left atrium can be decompressed before birth, the profound perinatal hypoxemia and acidosis and their associated morbidities may be prevented. If left atrial decompression can be achieved sufficiently early in gestation, adverse pulmonary venous remodeling may also be prevented. Physiologically, the earliest possible treatment of left atrial hypertension on diagnosis of atrial septal restriction should maximize the benefit of normalizing the developmental conditions for the pulmonary vasculature. In our experience, however, there are technical limitations to creating a large interatrial defect in the second trimester. Thus, for logistical reasons, we have focused on creating a large atrial communication. Given the currently available technological options, this can be pursued more aggressively in older and larger fetuses, and we thus tend to wait until the early-to-mid third trimester to perform this procedure. At the same time, we continue to search for technical and technological innovations that will allow earlier effective atrial septal opening.
We recently reported our experience with FCI in 21 fetuses with HLHS and an intact or highly restrictive atrial septum.9 Prenatal atrial septoplasty for this condition has also been reported by others with various monitoring and interventional approaches.10,11 In our experience, the atrial septum was crossed and an interatrial communication created in all cases, either with balloon dilation or placement of a stent. Fetal demise occurred in 2 cases; in both of these, a significant hemopericardium was noted at the conclusion of the procedure. Among neonates delivered after FCI for HLHS with significant atrial septal restriction, surgical survival remains quite poor (58%); however, in utero creation of an atrial septal defect does appear to have some benefit in terms of preoperative management, because neonates with an interatrial defect ≥3 mm after FCI had higher oxygen saturation at birth and were less likely to need urgent postnatal left atrial decompression.19 Although assessment of any postnatal survival benefit of FCI in patients with HLHS and an intact atrial septum will require more extensive experience, the potential to avert immediate postnatal deterioration has been demonstrated, and we consider FCI indicated for the comprehensive management of these high-risk fetuses.

Tuesday, January 13, 2015

The Beginning of Our Journey with HLHS

December 8 -- 19 Weeks

Blaine and I were so excited to finally have our first ultrasound and see if we were having a little boy or another little girl. We had the gender placed into an envelope, as we would reveal the gender at the end of the week on Carsyn's birthday in her birthday cake. After our ultrasound, our OB came in and gave us heart wrenching news, our baby had a heart defect. We weren't sure what it was specifically and would have to meet with a neonatal-perinatal specialist in a couple weeks. I had to get tests done to check for other types of genetic/chromosomal disorders, all of which came back low risk. We ended up having to cancel our appointment with the specialist due to Blaine's grandmother passing away, and rescheduled it for the New Year when we would be returning to Michigan from Ohio. Those 4 weeks were the longest 4 weeks of my life. I knew my baby had something wrong, I just didn't have any answers.

Kennedy 19 Weeks Gestation


January 7 -- 23 Weeks


Blaine's brother, Blake, came to watch Carsyn for the afternoon while Blaine and I met with the neo-peri specialist. We arrived to the doctor's office and proceeded back to the ultrasound room with much anticipation. Little did we know, our expectations for the best would be completely flipped and changed to the worst. The tech went through a full body ultrasound, complete with bone and brain measurements. We didn't hear much about the heart, so I assumed it really couldn't be too bad. No news is good news, right? The doctor then came in to do her own scans and see Kennedy for herself. She told us she did see a heart defect, then left the room for a few short moments to gather her notes. Upon returning, she gave us the news no parent wants to hear, "Your baby has a rare heart defect called Hypoplastic Left Heart. There isn't any known cause for this, it just has a 0.2% chance of happening." She explained to us the general ideas of the underdeveloped left heart and explained the treatments for it, all that are not easy to swallow. We had 4 options: abort the pregnancy (which I said was not an option), leave it untreated after birth (which she would not thrive or survive), go through a series of 3 staged surgeries (all of which are very serious), or a heart transplant. Speak of total shock. I had no emotions, no tears, no thoughts, nothing. Blank. I didn't know what to think. Blaine had to return to work, and I back home to Carsyn. We walked to our cars and it finally settled in. Our baby has a chance of not making it.

That night was one of the hardest times I've ever gone through, which I never thought I could endure anything worse than losing my mother unexpectedly in September 2008, when I was just 18 years old. How could this happen to me? What have I done so wrong in my life for God to try and take one more from me too soon. It's not fair. And I have learned life isn't fair, but how could this happen again. Trying to research and read blogs of others and cope with still the unknown of what this thing called HLHS exactly is, and to have to live with it all at once was overwhelming. I cried, and cried, and cried. It was almost like my tears would finally dry and I would start crying again. I would look at Blaine to see the tears in his eyes and it would break my heart again. How could this innocent baby have something so wrong? Why can't I take it from her? Sleep that night was hard. We both woke up with swollen eyes, but so happy to see Carsyn smiling and laughing and healthy, so thankful. Times were tough, I had some very low moments of the day while Blaine was gone at work. Since I've known Blaine, it's always been hard when he's been away, wether it be at work or across the United States at a track meet; for a few short hours of the day or entire weeks out of the year, I've always needed him. It hasn't been easy being home by myself, especially in these times, trying to comprehend everything. I waited by the phone to hear for an appointment to meet with our pediatric cardiologist for a day or two. Once that call came, I still had to wait for 2 weeks to finally get a confirmed diagnosis. We still have one week until then, and I'm not sure I will make it. I have become swamped with doctor appointments between three different doctors so quickly, all of which will become routine over the next few months.


Some questions I know people will be asking, I will answer below.
  • I am due May 2, but am hoping to make it at least to April 25 (39 Weeks). They will probably be inducing as Blaine's schedule has him traveling anywhere between Ohio to California in the surrounding weeks and I will have to be in Ann Arbor to deliver.
  • They encourage a natural birth, which is what we will plan on doing, unless they have to do a cesarean for other reasons.
  • We will be delivering at C. S. Mott Children's Hospital in Ann Arbor (University of Michigan Health Systems), where Kennedy will stay and be under some of the best HLHS doctors and surgeons in the world.
  • The first staged surgery called the Norwood Procedure will happen within the first week after birth, if she is big enough. The second surgery called the Glenn around 6 months, and the final one around 3 years called the Fontan.
As I am so heartbroken for my daughter, I have found a strength within myself and my family that we will fight. We have so much faith and confidence in God and the medicine Kennedy will be receiving from our amazing doctors and surgeons, and know she will be a little fighter and overcome these hard times we will endure.

Thank you everyone for joining us on our journey, and for all the love, support, prayers, and thoughts as we begin this long and surely winding road.

Kennedy 23 Weeks Gestation
Blaine, Granny, Carsyn, and I
In Loving Memory:
Carol "Granny" Renner
We Love and Miss You